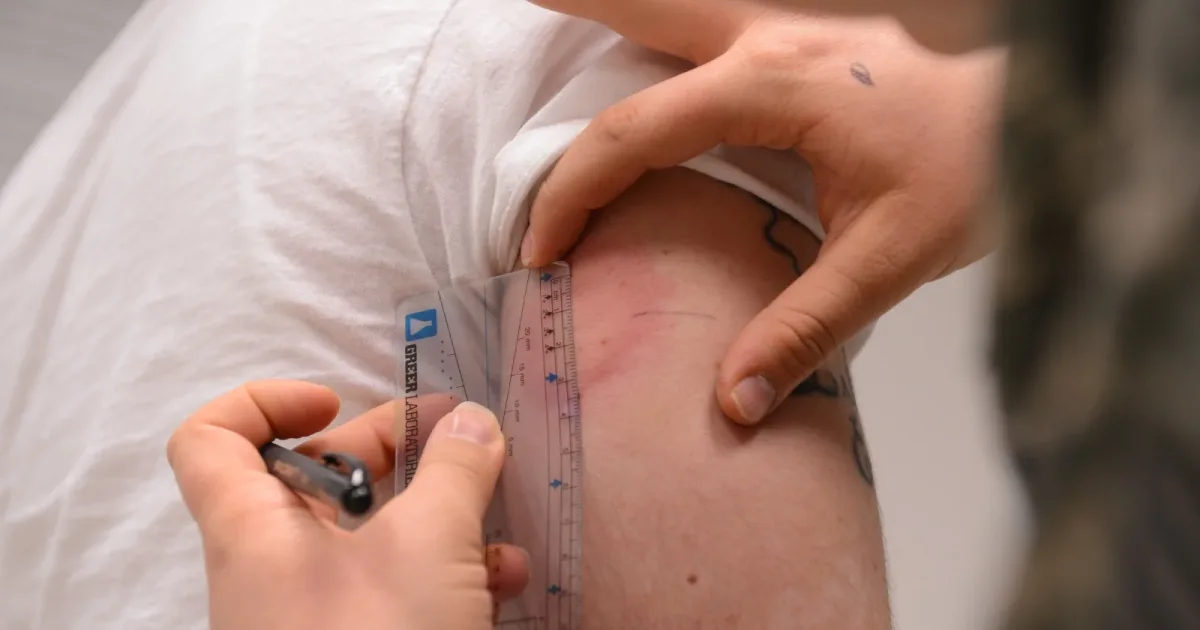
Researchers conducted three separate pre-registered trials in which 57 healthy adults underwent a standard histamine skin prick test on the forearm at least twice, with instructions to either focus on their arm or look away at video content. In roughly nine out of ten participants, keeping attention on the pricked site led to smaller inflammatory reactions. The cohort consisted predominantly of women with an average age in the mid-twenties, and the investigators note that a diminished response may not necessarily indicate beneficial immune regulation.
The procedure itself follows the protocol used in allergy clinics. A drop of histamine remains on the middle third of the left forearm for thirty seconds before a trained experimenter, unaware of the condition being tested, removes it with tissue. A lancet has already pierced the skin beneath. Over the following twenty minutes, a raised bump emerges and a ring of redness spreads outward; both are measured with a ruler at six time points.
Each participant completed the test at least twice, separated by three to five days and conducted at the same time of day. The sole variable between sessions was the attention instruction. When asked to maintain focus on the arm, the welt peaked at an average of 3.5 mm at the twenty-minute mark; when instructed to watch video clips, it reached 5.0 mm. Roughly nine in ten participants showed stronger reactions when their attention was diverted.
The findings appeared in Nature Human Behaviour on 17 August. Nofar Mizrachi and Liron Rozenkrantz of Bar-Ilan University conducted the work alongside Menachem Rottem from the allergy and clinical immunology division at Emek Medical Center in Afula. Their central claim is straightforward: the attention manipulation involved no medication, no training and no deception, yet it altered a local inflammatory response as it was unfolding.
Two sessions, three to five days apart
The standardized histamine skin prick test used here is identical to the procedure performed in allergy clinics. A reaction develops within minutes and reaches its peak between fifteen and twenty minutes. The raised bump is called wheal; the red halo is called flare. Measurements were taken at one, three, five, ten, fifteen and twenty minutes while researchers continuously recorded heart rate, skin conductance, skin temperature and pulse.
In the opening experiment, 37 participants kept their eyes on a screen during both conditions. One condition displayed a fixation cross with instructions to attend to sensations in the pricked hand, refocusing whenever the mind wandered. The other showed neutral video clips with instructions to attend to those instead. The flare followed the wheal: 10.6 mm under inward attention versus 14.0 mm under distraction. The difference at the twenty-minute peak was substantial by conventional standards, with a Cohen's d of 1.30. Post hoc analysis identified the first significant difference at the three-minute mark, where it was roughly half that magnitude, and it grew from there.
Participants were informed the experiment involved an allergy test but were not told what was being manipulated, and the histamine and lidocaine were never identified by name. At the conclusion, only eight of the 57 correctly identified the connection between attention and skin reaction, and their results matched everyone else's.
Both conditions saw the same thirty-seven shapes
Watching videos and staring at a fixation cross represent different cognitive tasks, so the authors designed a second experiment to address this confound. Twenty new participants received identical visual input in both conditions: the same sequence of 37 abstract shapes, each displayed for forty seconds in the same order. In one condition, each shape change served as a cue to redirect attention to the arm. In the other, participants judged whether the shape could exist in real life. Effort ratings on a post-task questionnaire showed no significant difference between the two conditions.
Reactions were roughly 1.6 times smaller under inward attention, and again 90 per cent of participants reacted more strongly under distraction. An objective verification confirmed the instructions had been effective: participants told to watch the shapes remembered them better.
One finding runs counter to the intuitive interpretation of these results. In the second experiment, participants rated itching and burning as stronger while attending to the arm. The reaction shrank even as the sensation of it intensified.
A smaller welt is not automatically a better one
Smaller wheal and flare measurements are conventionally interpreted as indicating more regulated immune activity, and this convention underpins the paper's framing. However, the authors also note that reduced magnitude "may not universally reflect beneficial regulation," since inflammation serves a protective function whose appropriate magnitude depends on context. Faster resolution may be advantageous in a sterile or excessive reaction. In an infection, the authors caution, excessive suppression could impair the body's defences.
The scope carries other limitations. This is histamine in the skin of healthy volunteers over twenty minutes, in a laboratory room under controlled light and temperature, with participants recruited between February 2024 and July 2025. Of the 57 analysed, 40 were women and the average age in each experiment fell in the mid-twenties. No molecular or cellular mediator was measured, so the link between attention and skin response remains an inference drawn from the observed pattern.
Two of the paper's findings require clarification about their status. The recovery analyses fell outside the pre-registration and the authors label them exploratory. This includes the comparison in which nearly 90 per cent of participants under inward attention showed a stable or shrinking welt between the fifteen- and twenty-minute measurements, compared to 46 per cent under distraction, in the first experiment. In the second experiment the same recovery comparison moved in the same direction but did not reach significance, which the authors attribute to the smaller sample size. Several secondary autonomic analyses that were pre-registered, including two standard heart-rate-variability measures, were not performed and are not reported. The replication presented here comes from the authors' own recruited cohort; the paper reports no independent replication.
Nothing in these experiments demonstrates that attention shortens an illness, alters the course of an allergy, or replaces any treatment. All participants were healthy volunteers, screened to exclude asthma, prior anaphylaxis, active infections, skin disease and antihistamine use, among other exclusions. The authors raise the possibility that habitually distracting from symptoms may contribute to conditions like chronic pain becoming persistent, then explicitly state this remains to be tested. This article reports on one paper, written by journalists. It carries no clinical standing. Decisions about a symptom, or about whether to continue taking an antihistamine or painkiller, belong with a physician.
Three sympathetic measures flat, one vagal index up
Skin conductance, heart rate, skin temperature and self-rated anxiety were all indistinguishable between conditions, with every comparison falling well short of significance. Pulse was recorded throughout and respiration in the second experiment; neither is reported.
Heart rate variability proved the exception, running higher during inward attention. The difference is modest, and heart rate variability is an indirect index of vagal activity, as the paper acknowledges. The pattern still points in one direction. Three sympathetic measures and a self-rated anxiety score remained unchanged while the single parasympathetic index shifted, and it continued shifting when the skin was numbed. On this evidence a vagal route offers the better interpretation and generalised stress a poor one.
Vagal traffic represents an established anti-inflammatory pathway. The parasympathetic system does not directly innervate the skin, so any contribution here operates through the multi-step reflex the paper describes. Cortisol and other hormonal routes were not measured at all.
Numbing the skin weakened the effect without removing it
To determine whether sensations themselves were responsible for the effect, 17 returning participants received 0.3 g of 5 per cent lidocaine cream applied over a marked three-by-three-centimetre patch before the prick, while maintaining attention on the arm. Topical anaesthetic is known to reduce the flare but not the wheal, so only the wheal was analysed.
Numbing made a difference. The wheal came back roughly a millimetre larger under lidocaine than with sensation intact in the same individuals. Yet it did not account for the entire effect: at 4.0 mm the numbed condition still fell short of the 4.9 mm those same 17 produced under distraction. On the recovery measure it did not separate from distraction at all, which represents a null result on seventeen people rather than a match, while fewer participants settled under lidocaine than with sensation intact. The authors interpret this as sensory signalling contributing specifically to the resolution phase when attention is directed inward. These recovery comparisons were not pre-registered either, and fall under the same exploratory label. Lidocaine does not block every fibre type, and the authors note that residual sensory input cannot be fully ruled out.
Distraction is already clinical technique
Looking away deliberately is established practice as well as habit, including virtual reality during painful procedures, and the paper suggests such strategies may in some contexts carry a physiological cost. That is the claim with something at stake, and these experiments cannot resolve it. Their design manipulated attention from the moment of the prick, so it does not fully separate an effect on how the reaction begins from an effect on how it resolves. The degree to which any of this generalises to infection, chronic inflammatory disease or autoimmune conditions remains, in the authors' words, unclear.
Earlier research did demonstrate an inflammatory response moving on command. Kox and colleagues trained participants to voluntarily activate the sympathetic nervous system during experimental endotoxaemia, which represents the opposite autonomic branch from the one implicated here, and the one this study's flat sympathetic readings make an unlikely explanation for its own effect. The forearm result went online this month, and the technique it questions is in use in clinics today, on people with a genuine reason to look away.
Source: Silicon Canals


